Published on:

 Reading Time: 5 min
 Scientific Articles
This evidence review synthesizes PubMed-indexed recent literature on gynecomastia-related risks, etiological drivers, preventive strategies and treatment outcomes. The included publications cover: pooled incidence of gynecomastia in hormone-modulating therapies, medication-related risk signals from meta-analyses, evidence on pharmacologic and radiotherapeutic prevention, outcome data on treatment effectiveness and consensus-level considerations relevant to clinical counseling and risk reduction.
 Table of Contents:
-
1
 How the evidence was selected: Criteria for the latest PubMed evidence
-
2
Medication-associated risks in gynecomastia: What patients most commonly experience
-
3
Hormonal imbalance as a central mechanism: Pathophysiologic variability
-
4
Rare but high-impact risk signal: Persistent or progressive gynecomastia
-
5
Preventive strategies: Evidence-based interventions that may reduce risk
-
6
Special-risk population: Gynecomastia in oncologic hormonal therapy
-
7
Pre and post-therapeutic risk reduction: Consensus-aligned principles
-
8
Key predictors of gynecomastia risk identified across the evidence
-
9
Clinical implications: What the evidence means for practice
-
10
Bibliography: The five latest PubMed-indexed articles considered
How the evidence was selected: Criteria for the latest PubMed evidence
A targeted PubMed search strategy was applied to identify recent systematic reviews and meta-analyses addressing gynecomastia incidence, risk factors and management. Priority was given to studies providing pooled quantitative estimates and a specific focus on gynecomastia rather than narrative discussion.
The final evidence set comprises a 2025 meta-analysis evaluating gynecomastia incidence in patients treated with androgen receptor pathway inhibitors, a 2024 network meta-analysis examining mineralocorticoid receptor antagonists and associated gynecomastia risk, a systematic review and meta-analysis of drug-induced gynecomastia, a systematic review assessing pharmacologic treatment effectiveness and a pooled analysis of preventive strategies in antiandrogen therapy.
Medication-associated risks in gynecomastia: What patients most commonly experience
Across pooled analyses, drug-induced hormonal imbalance emerges as the most consistent and clinically relevant driver of gynecomastia. The condition most frequently develops in the context of therapies that either increase estrogenic activity, suppress androgen action, or alter estrogen-to-androgen ratios.
Antiandrogens and hormone-modulating therapies
Meta-analytic data demonstrate a significantly increased incidence of gynecomastia among patients receiving androgen receptor pathway inhibitors compared with standard androgen deprivation therapy alone. This risk is dose and duration-dependent and often accompanied by breast pain, reinforcing the need for anticipatory counseling in oncologic settings.
Mineralocorticoid receptor antagonists
A network meta-analysis comparing spironolactone and eplerenone found that spironolactone is associated with a substantially higher relative risk of gynecomastia, reflecting its antiandrogenic and progesterone-agonist properties. This distinction is clinically meaningful when selecting long-term therapy for cardiovascular or endocrine conditions.
Hormonal imbalance as a central mechanism: Pathophysiologic variability
Gynecomastia represents a final common pathway of estrogen predominance at the breast tissue level. Meta-analytic and systematic evidence supports that this imbalance may arise from increased estrogen production, reduced androgen action, or altered receptor sensitivity.
The heterogeneity of underlying mechanisms explains variability in presentation, progression and reversibility across patient populations. From a risk-assessment perspective, this mechanistic variability constitutes a practical challenge: similar clinical appearances may reflect different endocrine drivers, influencing treatment responsiveness and recurrence risk.
Rare but high-impact risk signal: Persistent or progressive gynecomastia
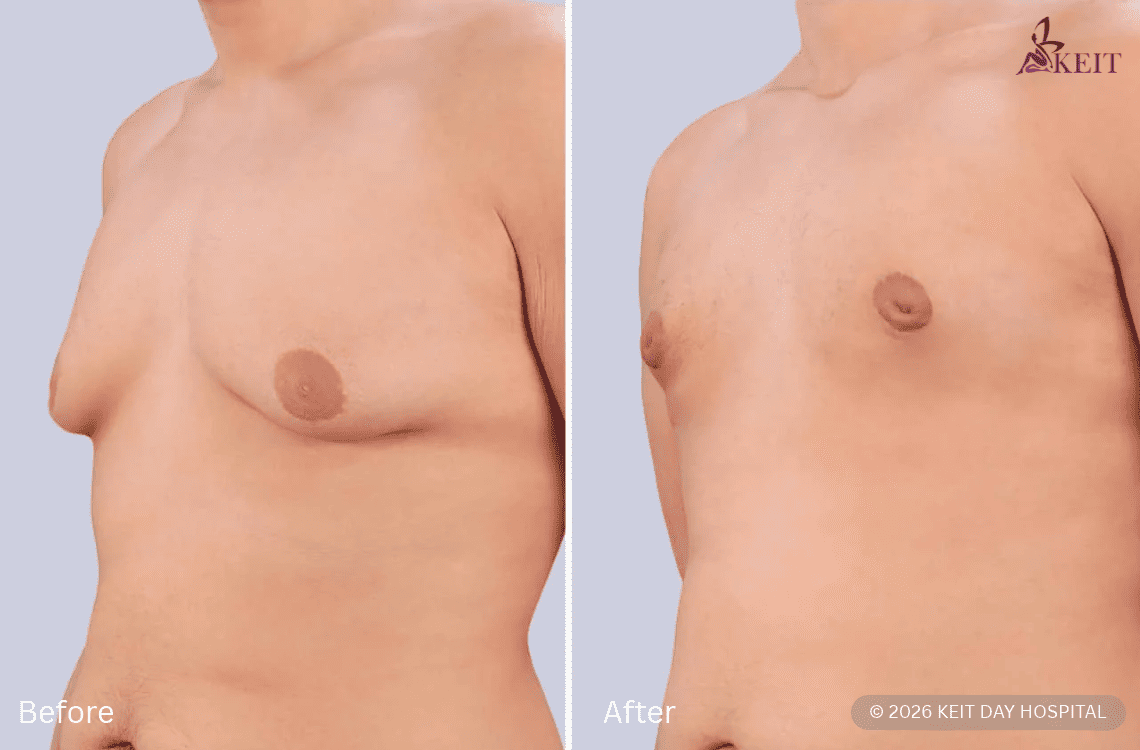
Although gynecomastia is often described as benign and self-limiting, pooled evidence identifies a subset of patients in whom breast tissue enlargement persists or progresses, particularly when the underlying hormonal driver is sustained.
In antiandrogen therapy, this persistence represents a clinically meaningful adverse outcome due to its impact on adherence, quality of life and psychological well-being. Clinical implication: Even when gynecomastia is not life-threatening, its durability and symptom burden justify proactive prevention strategies rather than reactive management alone.
Mortality signal and the importance of underlying etiologies
A nationwide Danish register-based cohort study adds a population-level perspective: males diagnosed with gynecomastia showed higher all-cause mortality overall, but the excess risk was driven mainly by those with pre-existing risk factors, not idiopathic cases. Cause-specific mortality was higher for malignant neoplasms and cardiopulmonary and gastrointestinal diseases, with a particularly strong association for liver disease in the risk-factor group. Practical implication: gynecomastia should trigger assessment for underlying systemic risk when predisposing conditions are present, not just cosmetic-focused management.
Preventive strategies: Evidence-based interventions that may reduce risk
A pooled analysis of randomized trials indicates that prophylactic interventions can meaningfully reduce gynecomastia incidence in high-risk settings.
- Tamoxifen prophylaxis significantly lowers the risk of gynecomastia and breast pain in patients receiving antiandrogen therapy by competitively inhibiting estrogen receptors in breast tissue.
- Prophylactic low-dose radiotherapy to breast tissue also reduces incidence compared with observation, although its use requires consideration of skin toxicity and patient preference.
- Aromatase inhibitors, by contrast, show inconsistent benefit across meta-analyses and do not appear to offer reliable protection.
This evidence supports positioning prevention as a core component of gynecomastia risk management in predictable high-risk scenarios.
Special-risk population: Gynecomastia in oncologic hormonal therapy
Patients undergoing hormonal treatment for prostate cancer represent a distinct high-risk group. Meta-analytic evidence shows that gynecomastia incidence is substantially higher in those receiving non-steroidal antiandrogens or androgen receptor pathway inhibitors than in those on standard androgen deprivation alone.
Practical implication: In this population, gynecomastia risk is therapy-dependent, foreseeable and often preventable, supporting shared decision-making around prophylaxis at treatment initiation rather than delayed intervention.
Pre and post-therapeutic risk reduction: Consensus-aligned principles
Across the evidence base, several modifiable factors consistently influence gynecomastia risk and burden:
- Early identification of high-risk medications.
- Consideration of alternative agents with lower estrogenic or antiandrogenic activity.
- Prophylactic anti-estrogen therapy in selected patients.
- Regular follow-up to detect progression or treatment-related distress.
Although formal consensus statements specific to gynecomastia are limited, these principles align closely with broader endocrine and oncologic best-practice frameworks.
Key predictors of gynecomastia risk identified across the evidence
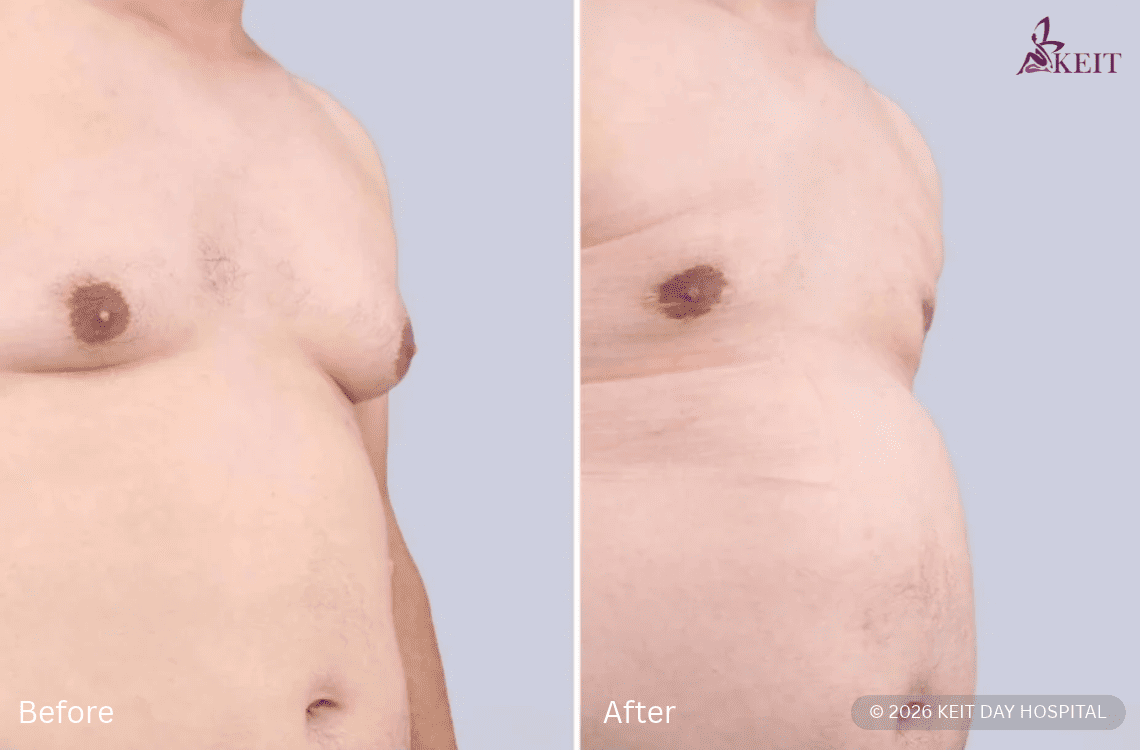
Across the included PubMed meta-analyses, the most consistent risk themes are:
- Medication-driven hormonal imbalance as the primary risk driver.
- Higher risk with antiandrogens and spironolactone compared with alternative therapies.
- Therapy duration and persistence of hormonal exposure.
- Indication-specific risk, particularly in prostate cancer treatment.
- Limited spontaneous regression when causative exposure continues.
Clinical implications: What the evidence means for practice
- Gynecomastia risk is predictable and stratifiable, particularly in drug-induced contexts.
- Preventive strategies are supported by pooled evidence and should be discussed proactively in high-risk patients.
- Choice of medication can meaningfully alter gynecomastia risk without compromising primary therapeutic goals.
- Persistent gynecomastia is not merely cosmetic and may affect adherence and quality of life, justifying early intervention.
Bibliography: The five latest PubMed-indexed articles considered
- Tsuboi I. Incidence, Management, and Prevention of Gynecomastia and Breast Pain in Patients With Prostate Cancer Undergoing Antiandrogen Therapy: A Systematic Review and Meta-Analysis of Randomized Controlled Trials. Eur Urol Open Sci. 2025. PMID: 39935942.
- Ho W.Y. Comparison of different medical treatments for primary hyperaldosteronism: A systematic review and network meta-analysis. Ther Adv Chronic Dis. 2024. PMID: 38511069.
- Trinchieri A. Drug-Induced Gynecomastia: A Systematic Review and Meta-Analysis. Arch Ital Urol Androl. 2021. PMID: 34933535.
- Berger O. Gynecomastia: A systematic review of pharmacological treatments. Front Pediatr. 2022. PMID: 36389365.
- Bräuner EV. Is male gynaecomastia associated with an increased risk of death? A nationwide register-based cohort study. BMJ Open. 2024. PMID: 38228396.