Published on:
 Modified on:

 Reading Time: 3 min
 Scientific Articles
This mini-review summarizes the current scientific evidence on the risks and complications of otoplasty for the correction of prominent ears, drawing primarily from systematic reviews and meta-analyses indexed in PubMed. The analyzed studies investigate the incidence of postoperative complications, compare different surgical techniques and identify key determinants influencing long-term outcome stability and the need for revision surgery.
 Table of Contents:
-
1
 Evidence selection and quality of included studies
-
2
Overall complication profile of otoplasty
-
3
Early and late complications: Temporal distribution
-
4
Influence of surgical technique on complication risk
-
5
Permanent sutures and late suture extrusion
-
6
Determinants of recurrence and revision surgery
-
7
Clinical implications and informed consent
-
8
Bibliography: Systematic reviews and key studies considered
Evidence selection and quality of included studies
The scientific literature on otoplasty includes fewer meta-analyses compared to other aesthetic surgical procedures. For this reason, this review prioritizes the highest-level evidence currently available, focusing on:
- systematic reviews with or without meta-analysis,
- studies reporting large aggregated patient cohorts,
- publications explicitly documenting complication rates and revision surgery incidence.
The included studies examine both pediatric and adult populations undergoing prominent ear correction using various techniques, including cartilage-sparing, cartilage-scoring and incisionless approaches. This allows for a comparative evaluation of the contemporary otoplasty risk profile.
Overall complication profile of otoplasty
Aggregated evidence reveals a relatively consistent pattern of complications. Most adverse events are mild to moderate and can be managed conservatively, while major complications remain uncommon. Typical incidence rates reported across systematic reviews include:
- Hematoma / postoperative bleeding: approximately 1–3%
- Local infection: <1–2%
- Skin healing problems or limited necrosis: 1–4%
- Suture irritation or extrusion: 1–3%
- Visible or hypertrophic scarring: 1–2%
- Recurrence or partial loss of correction: 4–6%
The overall need for revision surgery is reported to be below 5% in most aggregated case series.
Early and late complications: Temporal distribution
Clinical interpretation of otoplasty complications is enhanced when events are classified according to their time of onset.
Early complications (days–weeks) include:
- auricular hematoma,
- persistent edema,
- pain or localized hypersensitivity,
- wound infection.
These events are primarily associated with intraoperative hemostasis, postoperative dressing management and patient compliance during the early healing phase.
Late complications (months) include:
- extrusion of permanent sutures,
- residual asymmetry,
- partial recurrence of ear prominence,
- hypertrophic or visible scarring.
Late complications represent the main cause of aesthetic dissatisfaction and revision requests, despite the absence of functional impairment.
Influence of surgical technique on complication risk
Systematic reviews suggest that surgical technique does not significantly affect the incidence of major complications but may influence the type of late complications observed. Cartilage-sparing and cartilage-scoring techniques demonstrate:
- comparable rates of hematoma and infection,
- similar recurrence incidence.
Cartilage-sparing techniques are usually associated with reduced tissue trauma and greater reversibility, whereas cartilage-scoring techniques allow more aggressive reshaping in rigid cartilage at the cost of increased technical complexity.Incisionless techniques are associated with faster recovery and low early complication rates, but long-term outcomes may be more variable in patients with less malleable cartilage.
Permanent sutures and late suture extrusion
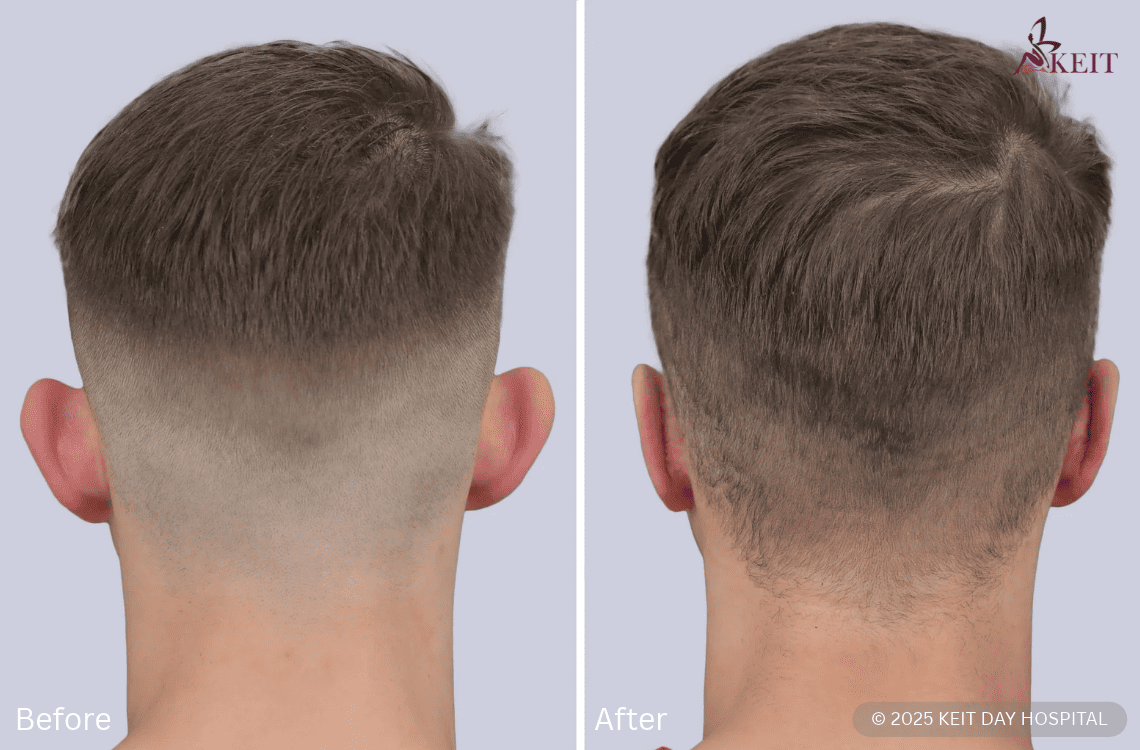
Extrusion of permanent sutures is one of the most characteristic late complications of otoplasty. Systematic reviews report an incidence of approximately 2%, with variability related to suture placement technique and anchoring depth. In most cases:
- extrusion is not associated with deep infection,
- management involves simple removal or repositioning under local anesthesia,
- aesthetic impact is limited when treated early.
Deep suture placement with adequate soft-tissue coverage significantly reduces this risk.
Determinants of recurrence and revision surgery
Recurrence represents the most clinically relevant complication of otoplasty. Evidence indicates that recurrence is primarily influenced by:
- cartilage rigidity and elastic memory,
- fixation technique used,
- distribution of traction forces,
- patient adherence to postoperative instructions,
- surgeon’s experience.
Most recurrences are partial and mild; only a minority require complete surgical revision.
Clinical implications and informed consent
Clinically, otoplasty should be considered a generally safe procedure, though not devoid of specific risks. Informed consent should emphasize:
- the possibility of recurrence or residual asymmetry,
- the risk of late suture extrusion,
- the potential need for secondary refinements,
- the distinction between true complications and aesthetic imperfections.
Careful patient selection, meticulous surgical technique and structured follow-up significantly reduce morbidity and improve long-term stability of results.
Bibliography: Systematic reviews and key studies considered
- Alanazi H. Complications of Cartilage-Sparing Otoplasty: A Systematic Review and Meta-Analysis. J Craniofac Surg. 2024.
- Sadhra SS. Complications after prominent ear correction: A systematic review of the literature. J Plast Reconstr Aesthet Surg. 2017.
- Limandjaja GC. Complications of otoplasty: a literature review. J Plast Reconstr Aesthet Surg. 2009.
- Teaima AA. Minimally invasive technique for correction of prominent ear. J Int Adv Otol. 2020.
- Mutaf M. A new cartilage-sparing procedure for correction of the prominent ear deformity: dermal anchor technique. Ann Plast Surg. 2020.